


Three times a week, for three to five hours each time, a hemodialysis machine filters the blood of a patient whose kidneys can no longer do it themselves. The machine keeps them alive. What it cannot do is address the accumulating symptom burden that hemodialysis patients carry through every session and every day between sessions. Research published in peer-reviewed nephrology and nursing journals between 2023 and 2025 measured what happens when Reiki is introduced into the hemodialysis setting specifically. Three separate studies, examining pain, fatigue, itching, anxiety, and quality of life, produced consistent and statistically significant findings that almost no one outside specialist renal nursing has read. This article reports those findings in full.
Table of Contents
What Hemodialysis Patients Actually Live With: The Numbers Most People Never See
The clinical focus of hemodialysis research has historically centered on survival outcomes: adequacy of dialysis, cardiovascular events, vascular access complications, and mortality. That focus has saved lives. What it has underweighted for decades is the day-to-day symptom burden that hemodialysis patients experience regardless of whether their dialysis numbers are adequate.
A multicenter cross-sectional study published in Scientific Reports in 2025 assessed symptom prevalence in hemodialysis patients using the Dialysis Symptom Index. The most prevalent symptom was fatigue, affecting 84.3 percent of patients. Dry skin affected 56.9 percent. Itching affected 52.9 percent. Difficulty concentrating was reported by 54.9 percent. The symptoms rated highest in severity included instability of the legs at a mean severity score of 8.0 out of 10, bone and joint pain at 7.1, and difficulty sleeping at 7.0.
A global systematic review and meta-analysis published in PLOS Medicine confirmed that fatigue is the most prevalent and second most severe symptom across all dialysis populations. The adjusted severity score for fatigue in dialysis patients was 51.5 on a standardized scale, compared to a prevalence of 34 percent in healthy controls. Pain was identified as the single most severe symptom in the dialysis population overall.
A separate review of 591 hemodialysis patients found that pain, fatigue, lack of wellbeing, and depression were the only independent predictors of quality of life in this population, together accounting for 38.5 percent of the variation in physical health scores and 42.5 percent of the variation in mental health scores. These symptoms are not peripheral complaints. They are the primary drivers of how well or how badly a hemodialysis patient is actually living.
The average hemodialysis patient carries between 6 and 20 concurrent symptoms, according to comprehensive reviews cited in Frontiers in Public Health. Of those, the pharmacological options for many, particularly fatigue, itching, and the anxiety associated with prolonged treatment dependence, remain limited. This is the clinical gap that the following research addresses.

Disclaimer: The information in this article is intended for educational purposes only and does not constitute medical advice. Reiki and energy healing are complementary practices and are not a substitute for professional medical treatment. Always consult a qualified healthcare professional for medical concerns.
Study 1: Pain, Fatigue, and Itching in 74 Patients Across Three Dialysis Centers (2025)
The most comprehensive hemodialysis Reiki study published to date was authored by Esra Baser Akin and colleagues and published in Hemodialysis International in April 2025 (Volume 29, Issue 2, pages 201 to 213, DOI: 10.1111/hdi.13203, Epub February 5, 2025, PubMed ID: 39908578). The study used a randomized controlled design and was conducted across three dialysis centers simultaneously, which is methodologically stronger than single-center studies because it reduces the risk that results reflect site-specific factors rather than the intervention itself.
Who Was Studied and What Was Done
74 hemodialysis patients participated in total, with 37 assigned to the Reiki intervention group and 37 assigned to the control group receiving routine hemodialysis treatment alone. A total of 10 Reiki sessions were administered to patients in the intervention group, delivered twice a week for five weeks. The three outcomes measured were pain, fatigue, and itching: three of the most prevalent and least pharmacologically addressable symptoms in the hemodialysis population.
What the Study Found
The published results demonstrated statistically significant reductions in all three measured symptoms in the Reiki group compared to the control group. Pain levels, fatigue scores, and itching severity all decreased meaningfully in patients who received the Reiki sessions over the five-week protocol. The control group showed no comparable improvements in any of the three outcomes over the same period.
The itching finding deserves specific attention. Uremic pruritus, the chronic itching that affects more than half of all hemodialysis patients, is one of the most distressing and least effectively treated symptoms in renal care. Current pharmacological options are limited, often inadequate, and carry their own side effect profiles. A non-pharmacological intervention producing a statistically significant reduction in itching severity in a randomized controlled trial in a dialysis population is a clinically meaningful finding that renal nurses and nephrologists should know about. Most do not, because this research does not yet reach general nephrology education or standard dialysis care training.
Study 2: Fatigue and Anxiety in Hemodialysis Patients (Holistic Nursing Practice, 2024)
A randomized controlled study published in Holistic Nursing Practice in January to February 2024 (Volume 38, Issue 1, pages 26 to 31, DOI: 10.1097/HNP.0000000000000625, PubMed ID: 37966988) was conducted at the hemodialysis clinic of Siirt State Hospital in Turkey. The study was authored by Zeliha Buyukbayram Genc from Siirt University and Dr. Citlik Saritas from Inonu University between January and August 2021.
Design and Outcomes
The study was designed as a randomized controlled trial investigating the effects of Reiki specifically on fatigue and anxiety in hemodialysis patients. Both outcomes were measured using validated clinical instruments before and after the Reiki intervention period.
Results
Statistically significant reductions in both fatigue and anxiety were found in the Reiki group compared to the control group. The study’s conclusion recommended Reiki as a complementary approach for managing fatigue and anxiety in dialysis patients, noting its safety and non-invasive nature as factors that make it particularly appropriate for a population who are already managing complex medication regimens and multiple comorbidities.
The anxiety finding in this population carries specific clinical weight. Hemodialysis is not simply a treatment. It is a life-organizing constraint. Patients structure their entire week around three dialysis sessions. They cannot travel freely. Their diet is severely restricted. Their social life narrows. The existential weight of dependence on a machine for survival produces a form of anxiety that is both understandable and insufficiently addressed by standard renal care. A non-pharmacological intervention that measurably reduces that anxiety during and around the dialysis sessions themselves addresses a need that is real, documented, and currently unmet for the majority of the hemodialysis population.
Study 3: Pain Severity and Quality of Life, Double-Blind Randomized Controlled Trial (Published 2025)
A comparative study examining the effects of Reiki Levels 1 and 2 on pain and quality of life in hemodialysis patients was authored by Sultan Cecen and Sultan Tasci and published in the Journal of Holistic Nursing in November 2025 (DOI: 10.1177/08980101251393300, Sage Journals). The study registered on ClinicalTrials.gov under NCT06063616, was designed as a double-blind, randomized controlled trial using a pretest-posttest design at Mersin University.
What Made This Study Methodologically Important
The double-blind design places this study among the most methodologically rigorous Reiki studies conducted in any clinical population. In a double-blind trial, neither the person delivering the assessment nor the patient knows which study arm the patient is in at the point of outcome measurement, which controls for both observer bias and patient expectancy effects. The study also specifically compared the effects of Reiki Level 1 versus Reiki Level 2, making it the first hemodialysis study to examine whether the level of practitioner training affects outcomes in this population.
What It Found
The study found that four consecutive 20-minute Reiki Level 2 sessions produced statistically significant improvements in both pain levels and quality of life scores compared to the control condition. The assessment of whether Level 1 and Level 2 produce differentially significant effects in this population provides a baseline of comparative data that can inform how dialysis units structure future Reiki programs if they choose to implement them.
What a Hemodialysis Treatment Session Actually Looks Like from the Patient’s Perspective
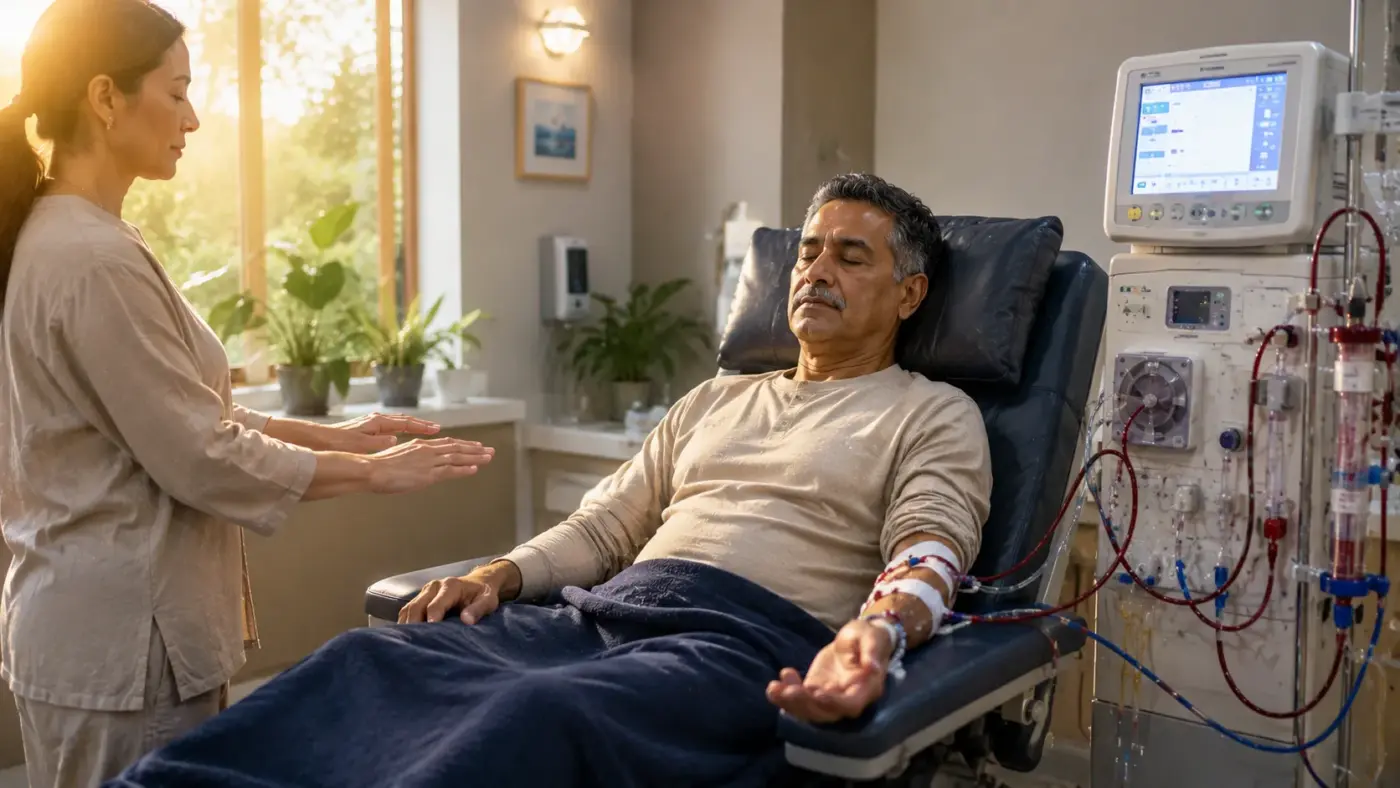
To understand why these research findings matter practically, it helps to understand what a hemodialysis session is like from the inside. A patient arrives at the dialysis center, typically three times a week. Needles are inserted into an arteriovenous fistula in the arm. Blood flows out through tubing, passes through a dialyzer that filters waste products and excess fluid, and returns to the body. This continues for three to five hours.
During those hours, the patient is largely immobile. They may read, watch television, or sleep. They are tethered to a machine. Many experience intradialytic symptoms: muscle cramps, hypotension, nausea, headaches, and the persistent fatigue that does not lift when the session ends but continues into the post-dialysis recovery period that can last several hours. Anxiety about access complications, about the machine alarming, about whether this session will go smoothly, runs as a background frequency through the entire experience for many patients.
This is the environment in which Reiki was administered in these studies, either during the dialysis session itself or in the clinic setting around it. The practical reality is that a patient seated in a dialysis chair is an accessible recipient for hands-on or near-body Reiki. The session duration is fixed and the patient is already stationary. From a logistical standpoint, the dialysis session is one of the most practically suitable clinical contexts for Reiki delivery that exists in medicine.
Why This Population Has Been Underserved by Complementary Therapy Research
Students often ask me why some of the most compelling Reiki research involves populations that most people rarely think about in the context of energy healing: dialysis patients, autism therapists, frontline healthcare workers. My answer is that the research tends to go where the unmet need is greatest and where the conventional pharmacological toolkit is most limited.
In hemodialysis specifically, the symptom burden is severe, the pharmacological options for the most prevalent symptoms are genuinely inadequate, and the patients are captive in a clinical setting three times a week in circumstances that make complementary therapy delivery logistically straightforward. The researchers who conducted these three studies recognized all of those factors. The results they produced are consistent across all three study designs, all three research groups, and all three countries in which the research was conducted. Turkey, where all three studies originated, has produced some of the most methodologically rigorous Reiki research in the world over the past five years, a pattern worth noting for anyone tracking where the strongest evidence base is being built.
The Clinical Case for Integrating Reiki into Dialysis Units
The cumulative evidence from these three studies supports a specific and actionable recommendation: Reiki delivered by trained practitioners, either during dialysis sessions or in the immediate clinical context surrounding them, reduces pain, fatigue, itching, and anxiety in hemodialysis patients at a statistically significant level across multiple randomized controlled trial designs.
The practical implementation pathway is not complicated. Dialysis units that employ nurses with Reiki training, or that partner with volunteer Reiki practitioners, can offer sessions during treatment time without disrupting clinical workflow. The patient is already seated and stationary. A 20-minute Reiki session, which was the standard duration used across these studies, fits within the treatment window without extending the patient’s time in the unit. No additional clinical infrastructure is required.
For renal care professionals reading this, the question the research poses is direct: if three randomized controlled trials across three dialysis centers have found statistically significant reductions in the three most pharmacologically resistant symptoms in your patient population, what is the barrier to piloting this intervention?
I have found, working with practitioners who support patients in chronic illness settings, that the most common barrier is not scepticism about the evidence. It is simply that the evidence has not reached the people who make clinical decisions in dialysis units. These studies are published in specialist journals, in a language, Turkish, that most Western renal nurses do not read, and in a field, complementary medicine, that sits at some distance from standard nephrology education. That is the gap this article is attempting to address.
What This Research Does Not Claim
None of the three studies claims that Reiki replaces dialysis, improves renal function, or reduces the frequency of treatment sessions required. All three investigated symptom management within the existing hemodialysis care structure, not as an alternative to it. The appropriate framing is the one all three research teams used: Reiki as a complementary symptom management tool for a population whose symptom burden significantly exceeds what pharmacological care currently addresses.
The sample sizes across the three studies, ranging from 37 to 74 participants per arm, are sufficient for meaningful pilot and controlled trial findings but are not large enough to make population-level treatment recommendations without further replication. The consistent direction of findings across three independent research groups is encouraging. The next step the field needs is a larger, multi-center trial in a Western dialysis setting with standardized outcome measures and sufficient power to detect clinically meaningful differences across the full symptom profile.







